Now Playing
AATD is better understood as a genetic predisposition than a single disease. Genotype, codominant inheritance, and environmental exposure together shape who develops lung or liver disease and how severe it becomes.
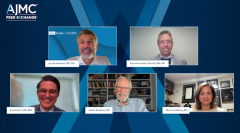
Welcome back to another AJMC Peer Exchange series. In "AATD Genetics: Z Allele, Codominance, and Predisposition Risk," moderator Ryan Haumschild, PharmD, MBA, MS is joined by Igor Barjaktarevic, MD, PhD, Brooks Kuhn, MD, MAS, Monica Goldklang, MD, and Robert Sandhaus, MD to open the series on alpha-1 antitrypsin deficiency.
Dr. Haumschild outlines three goals for the program: reviewing the disease state, examining the current treatment landscape, and looking ahead to emerging therapies that could change treatment paradigms. He then asks each panelist to introduce themselves. Dr. Barjaktarevic is a pulmonologist and intensivist at UCLA with a clinical and research focus on airway disease and AATD. Dr. Kuhn is an associate professor at UC Davis in Sacramento. Dr. Goldklang, a pulmonologist and intensivist at Columbia University, runs the Alpha-1 Foundation Clinical Resource Center and takes part in many clinical trials. Dr. Sandhaus has run the Alpha-1 program at National Jewish Health for 46 years and directs several national Alpha-1 organizations.
Dr. Haumschild then asks Dr. Barjaktarevic how he explains, for a managed care audience, why carrying two copies of the Z variant carries a different clinical risk than carrying one. Dr. Barjaktarevic first challenges the framing of AATD as a rare disease. He argues that it is neither truly rare nor a single disease, but a predisposition to a variety of conditions. The disorder stems from mutations in the SERPINA1 gene, and many different mutations have been described. How the disorder eventually presents depends on those genetic factors combined with environmental influences over time, which makes the picture highly heterogeneous.
He explains that AATD follows a codominant inheritance pattern, meaning each of a person's two genes produces its own alpha-1 antitrypsin protein. When both genes are abnormal, the body cannot produce enough protein to balance proteases and antiproteases, and the risk of disease rises. The Z allele, which causes severe deficiency, is the mutation with the most supporting data. People who are homozygous for Z face the greatest risk. Even so, he notes that carrying a single Z allele still raises risk compared with a normal genetic setup.
The next episode in this series, "Diagnosing AATD: Levels, Genotype, and the Diagnostic Gap," features Dr. Barjaktarevic explaining why a single level cannot capture risk, followed by Dr. Kuhn on what the diagnostic gap means for payers.