
Opinion|Videos|September 30, 2026
Diagnosing AATD: Levels, Genotype, and the Diagnostic Gap
A serum level is a snapshot, while genotype is the blueprint. Relying on levels alone misses carriers and mislabels patients, and the resulting diagnostic gap carries real clinical and economic costs.
Advertisement
Episodes in this series
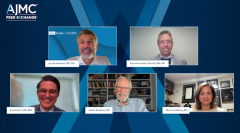
"Diagnosing AATD: Levels, Genotype, and the Diagnostic Gap" takes up a question many clinicians never learn to answer: which test to order, and what it can and cannot show.
Dr. Haumschild asks why genotype should be evaluated alongside AAT levels and what added risks exist for heterozygous patients. Dr. Barjaktarevic says providers who are enthusiastic about testing often do not know which test to pick. Options include a serum level, phenotyping, genotyping, and full gene sequencing. He describes the level as a snapshot and the genotype as the blueprint.
He gives several reasons the distinction matters. The normal range is wide, and AAT is an acute phase reactant, so levels can roughly double when a person is sick. One patient on a bad day and another on a good day may look indistinguishable. Standard levels also measure the amount of circulating protein rather than its function. Some mutations cause dysfunction as well as deficiency, and the Z variant causes both. A level works as a screen and will usually catch the most severely deficient patients. However, the exact type of deficiency and the carrier state are often missed without genotype or phenotype testing.
Dr. Haumschild then turns to Dr. Kuhn, noting that fewer than 10 percent of the roughly 100,000 Americans with severe AATD are estimated to be diagnosed. Dr. Kuhn says the number is credible. A cross-sectional analysis of the UK Biobank identified only 6.8 percent of ZZ individuals, so 10 percent may even be an overestimate.
He rejects the idea of waiting for symptoms. Underdiagnosis does not mean low cost, because patients bounce between clinicians and collect labels of asthma, COPD, and bronchiectasis. That pattern produces unplanned visits without addressing the core problem. Early diagnosis also creates a prevention opportunity, since patients told they have a genetic predisposition are more likely to quit smoking. Because lung and liver tolerate damage for a long time, symptoms often mean injury has already occurred.
Up next, in "AATD Is Not Just COPD: Why Testing Rates Stay Low," Dr. Goldklang explains why not every patient with AATD looks like a smoker with emphysema, and Dr. Sandhaus explains why guideline-recommended testing still falls short.
Advertisement
Related to this article
A network meta-analysis found vibegron outperformed mirabegron and tolterodine on several OAB efficacy measures but had higher odds of adverse events.

A US modeling study found tirzepatide and semaglutide cost-effective for MASH, while resmetirom exceeded the $100,000/QALY threshold.

Expert panel discussions covered AI and community access, chronic lymphocytic leukemia, myeloma, and breast and lung cancers.

The analysis found a nonlinear association between systemic inflammation and overactive bladder, with stronger links at higher inflammation levels.
A real-world study found that adding a GLP-1 to SGLT2 inhibitor therapy was associated with lower kidney, cardiovascular, and mortality risks in CKD.

In experiments at MD Anderson, rising CD70 helps mantle cell lymphoma evade immunity; a CD70×CD3 bispecific restores T-cell killing and prolongs survival in resistant models.

Upper-extremity synovial sarcoma required more staged surgery, while lower-extremity disease carried more complications and metastases.

In the US alone, 1.1 million individuals are living with the progressive neurodegenerative movement disorder, and 90,000 are diagnosed each year.
Advertisement
Advertisement
Trending on AJMC
1
Medicare Cap Eases Patient Costs as Negotiation Squeezes Practices
2
Drug Price Drives Value of MASH Therapies More Than Efficacy
3
IRA, 340B, Medicaid: The Policy Pressures on Community Oncology
4
PBM Satisfaction Stalls as Net Promoter Score Turns Negative
5